The 10-Minute Heart Scan That Can Save Your Life
Most of us know our blood pressure. Many of us know our cholesterol numbers. But very few people know what is actually happening inside the arteries that feed their heart. That is a shame, because those arteries can quietly fill with plaque for decades without causing a single symptom.
Today, a quick and painless scan can show doctors how much plaque has built up in your heart arteries, long before it causes chest pain or a heart attack. In March 2026, America's leading heart organizations released new cholesterol guidelines that give this kind of heart imaging a bigger role than ever before. Here is what you need to know about heart artery scans, who should consider one, what the process looks like, and what your results really mean.
Why Your Heart Arteries Deserve Attention
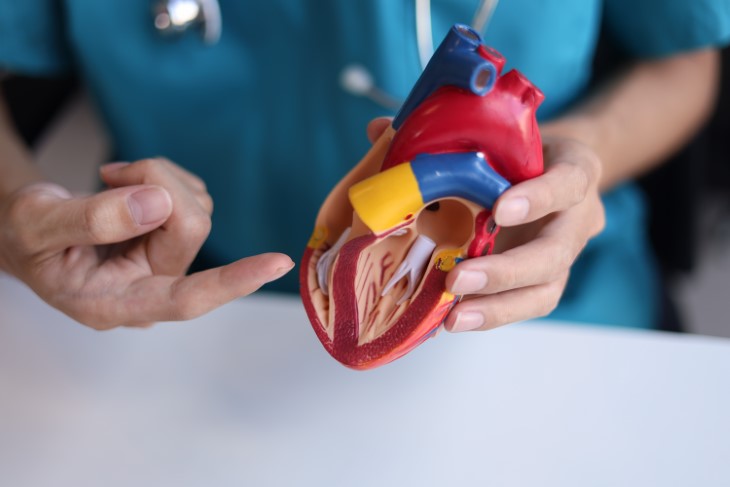
Your heart is a muscle, and like any muscle, it needs a steady supply of oxygen-rich blood. That blood arrives through the coronary arteries, a network of vessels that wraps around the outside of the heart. Over the years, cholesterol, fat, calcium, and inflammatory cells can collect in the walls of these arteries, forming what doctors call plaque. This process is known as atherosclerosis, and when it affects the heart arteries, the result is coronary artery disease.
The numbers are sobering. In the United States, coronary heart disease affects more than 20.5 million adults and causes more than 370,000 deaths every year. It is the single largest cause of death among all heart and blood vessel diseases, responsible for about 38% of those deaths. In fact, heart disease and stroke together claimed more American lives in 2023 than all forms of cancer and chronic lung disease combined.
Roughly every 40 seconds, someone in the United States has a heart attack. That adds up to about 605,000 first heart attacks and another 200,000 repeat attacks each year. The average age of a first heart attack is about 65 for men and 72 for women.
The Problem: Plaque Doesn't Announce Itself
Here is the most troubling part. Plaque builds up silently. You can feel perfectly healthy, walk your dog every morning, and still have significant buildup in your heart arteries. About half of men and nearly two-thirds of women who die suddenly from coronary heart disease never had any previous symptoms. For many people, the very first sign of heart disease is a heart attack.
There is another surprise. Many heart attacks do not come from arteries that were already badly narrowed. They often start when a plaque that was only causing a mild or moderate narrowing suddenly cracks open. The body rushes to repair the crack by forming a blood clot, and that clot can block the artery completely within minutes. This is one reason why a traditional treadmill stress test, which looks for arteries that are already narrowed enough to limit blood flow, can come back normal in someone who still has plenty of dangerous plaque.
That is exactly the gap heart artery imaging is designed to fill. Instead of asking whether blood flow is already limited, it asks a simpler and earlier question: is plaque there at all, and how much?
How Common Is Plaque as We Age?
Plaque becomes more common with every passing decade. In one of the largest American studies on the subject, which followed thousands of adults between the ages of 45 and 84, about 60% of men and nearly 40% of women already had measurable calcium in their heart arteries. Calcium is a telltale sign of plaque.
By age 75, only about 1 in 9 people have completely clean arteries on a calcium scan, and by age 90, more than 95% of people have at least some calcium. Men tend to develop plaque earlier than women, usually by about 10 years, though women catch up after menopause.
The good news is that finding plaque early gives you time to act. Plaque can be stabilized, and its growth can be slowed dramatically with the right lifestyle changes and medications.
The Main Types of Heart Artery Scans
When people talk about "mapping" their heart arteries, they usually mean one of three tests. Each has a different purpose.
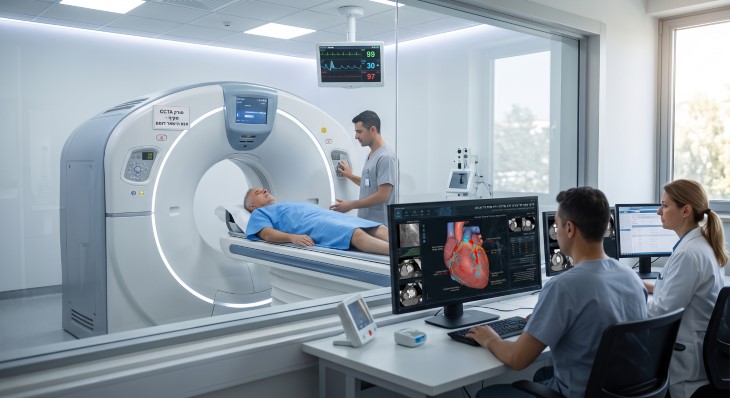
1. The coronary calcium scan (calcium score test). This is the most common screening test for people without symptoms. It is a quick, low-dose CT scan that detects hardened, calcified plaque in the heart arteries and turns it into a single number called your calcium score. No needles, no dye, and no special preparation are required.
2. Coronary CT angiography. This is a more detailed CT scan that uses contrast dye injected through a vein in your arm. It creates a detailed three-dimensional picture of the inside of your heart arteries, showing both hard, calcified plaque and soft plaque, which the calcium scan cannot see. It can also estimate how narrow each artery has become. Doctors usually order this test for people who have chest pain or other symptoms, rather than as a general screening tool.
3. Cardiac catheterization (invasive angiography). This is the traditional gold standard. A thin tube is threaded through an artery in the wrist or groin up to the heart, and dye is injected while X-ray images are taken. It is usually reserved for people with symptoms, abnormal test results, or a suspected heart attack. One advantage is that if a serious blockage is found, a cardiologist can often open it with a balloon and stent during the same procedure.
Does Scanning Actually Prevent Heart Attacks?
It is a fair question. A scan by itself does not unclog anything. Its power lies in what happens next.
A large study in Scotland followed more than 3,500 people who came to cardiology clinics with chest pain. Half received standard care, and half also received coronary CT angiography. After 5 years, the scanned group had about 41% fewer deaths from heart disease and nonfatal heart attacks. After 10 years, the benefit was still there, with serious heart events occurring in about 8.3% of the scanned group compared with 10.3% of the standard care group.
Interestingly, the scanned group did not end up having more stents or bypass surgeries over the long run. The difference came from prevention. When patients and doctors could actually see the plaque, they were more likely to start cholesterol-lowering medication and other protective treatments, and to stick with them. There is something about seeing your own arteries on a screen that makes the risk feel real.
Who Should Consider a Calcium Scan?
A calcium scan is not recommended for everyone, and the new 2026 guidelines make clear that it is not meant for universal screening. It is most useful when you and your doctor are unsure whether you need preventive treatment such as a statin.
Good candidates are generally people in their 40s, 50s, or 60s who have never had a heart problem but do have risk factors such as:
Borderline high cholesterol
Prediabetes
Excess weight
High blood pressure
A current or past smoking habit
A parent or sibling who had heart disease at a young age
For women, a history of early menopause, preeclampsia, or diabetes during pregnancy
Inflammatory conditions such as rheumatoid arthritis, lupus, or psoriasis
On the other hand, the test is usually not helpful for people who have already had a heart attack, a stent, or bypass surgery, since their risk is already known to be high. It is also not needed for people with very high LDL cholesterol (190 mg/dL or above), who need treatment regardless, or for people at very low risk, such as most adults under 40.
What the Process Looks Like
If you have never had a calcium scan, you may be surprised by how simple it is. The entire appointment usually takes 10 to 15 minutes, and the scan itself takes only a few seconds.
Before the scan: There is no need to fast. You may be asked to avoid caffeine and smoking for a few hours beforehand, since both can speed up your heart rate and blur the images. Wear comfortable clothing without metal, or expect to change into a gown.
During the scan: A technician places a few small sticky pads on your chest to track your heartbeat, so the machine can take pictures between beats when the heart is still. You lie on your back on a table that slides into the open, ring-shaped CT scanner. You will be asked to hold your breath for several seconds while the images are taken. There are no needles and no dye.
After the scan: You can go straight back to your normal day. A radiologist or cardiologist reviews the images, and your doctor typically receives the results within a few days.
Radiation: The dose is low, roughly 1 to 2 millisieverts, which is similar to a mammogram and equal to a few months of the natural background radiation we all absorb from the environment.
Cost: Because it is considered a screening test, most insurance plans, including Medicare, usually do not cover a calcium scan. The good news is that it is relatively affordable, typically between $75 and $300 out of pocket, and many imaging centers offer a flat cash price. Some centers accept self-referrals, but it is best to go through your doctor so the results are interpreted in context.
Coronary CT angiography is a slightly longer process. You will have an IV placed for the contrast dye, and you may be given medication to slow your heart rate for clearer images. The radiation dose is somewhat higher, and people with kidney problems or a dye allergy need special precautions. When ordered for symptoms, it is usually covered by insurance.
What Your Calcium Score Means
Your result will be a number, usually called an Agatston score after the doctor who developed the method. Your report may also include a percentile, which compares your score with other people of the same age, sex, and background. Under the 2026 guidelines, each score range is now linked to specific cholesterol goals.
Score of 0: No calcified plaque was found. Your risk of a heart attack over the next several years is very low. Many people in this group can safely hold off on statins, unless they smoke, have diabetes, or have a strong family history of early heart disease. The guidelines suggest considering a repeat scan in 3 to 7 years.
Score of 1 to 99: Mild plaque is present. Heart disease has officially begun, even if it is early. Doctors generally aim to bring LDL cholesterol below 100 mg/dL, often with a statin and lifestyle changes.
Score of 100 to 299: Moderate plaque. Your risk is meaningfully higher. The goal is to cut LDL cholesterol by at least half and bring it below 70 mg/dL.
Score of 300 or higher: Extensive plaque and a high risk of a heart attack. The target LDL is below 55 mg/dL, which often requires a combination of medications.
Score above 1,000: Very extensive plaque. People in this range are treated as aggressively as those who have already had a heart attack.
One important point: a high calcium score does not automatically mean you have a blocked artery or need a stent. It measures how much plaque you have overall, not how narrow any single artery is. If you have no symptoms, the main response to a high score is usually medication and lifestyle changes, not surgery. If you do have symptoms, such as chest pressure or unusual shortness of breath during activity, your doctor may order further testing.
A Bonus Many People Miss
If you have ever had a regular chest CT scan, for example for lung cancer screening or to check a cough, the radiologist may have noticed calcium in your heart arteries. Under the new guidelines, calcium spotted on an ordinary chest CT can now be used to guide treatment decisions. If you have had such a scan, it is worth asking your doctor whether any coronary calcium was mentioned in the report. Keep in mind that the reverse is not true: a regular chest CT that shows no calcium is not a substitute for a proper calcium scan.
The Limitations Worth Knowing
No test is perfect, and a calcium scan has a few blind spots. It only detects calcified plaque, so it can miss younger, softer plaque, which is sometimes the more unstable kind. That is why a score of zero is reassuring but not a lifetime guarantee, especially for smokers and people with diabetes.
The scan can also pick up incidental findings in the lungs or other nearby structures, such as small nodules. Most turn out to be harmless, but they can lead to follow-up scans and some worry. It is a good idea to discuss this possibility with your doctor beforehand.
Finally, a calcium scan does not replace the basics. Blood pressure, cholesterol, blood sugar, and a simple one-time blood test for lipoprotein(a), an inherited type of cholesterol particle, all remain important pieces of the puzzle.
What to Do After You Get Your Results
Whatever your score, the steps that protect your arteries are the same, and they work at any age:Stop smoking, which is the single most powerful step for your arteries:
Aim for about 150 minutes of moderate activity a week, such as brisk walking
Eat plenty of vegetables, fruit, whole grains, beans, nuts, and fish, and limit processed meats and sugary foods
Keep your blood pressure and blood sugar under control
Get 7 to 9 hours of sleep a night
Take prescribed medications consistently, even when you feel fine.